“Obama Bright” a portrait of Barack Obama in acrylics and graphite with Swarovski crystals that apparently didn’t please our leader…Or he doesn’t have the common courtesy to thank me for it.
I am serious. I sent this portrait of Barack Obama to the White House in January 2014, and only just received a small form card, saying nothing personal, only that the “gift was received” from the American people, thank you very much…and Obama and Michelle’s signatures scrawled on the bottom, as if that means anything to me. He clearly didn’t send it to me personally to thank me for any portrait. WTF. I spent HOURS drawing that very closely detailed portrait, first in graphite, then I had to copy it, before I hand painted the background and certain details over the copy. I am really really upset. EVERYONE i know here loved that portrait and encouraged me to send it to Obama, but I was worried that he wouldn’t like it or perhaps it would be destroyed by the Secret Service because of looking for anthrax or something stupid like that under the swarovski crystal that are glued on the background. Like i said, WTF. I am never sending anyone important any of my artwork again. The wealthy and important clearly don’t get the rules of common courtesy, do they?
I THOUGHT THIS WAS INCREDIBLY WELL WRITTEN AND IMPORTANT INFORMATION. SEE CREDITS AT THE BOTTOM. Posted on January 12, 2014 by annecwoodlen THINGS YOUR DOCTOR SHOULD TELL YOU ABOUT ANTIDEPRESSANTS September 12, 2012 By Paul W. Andrews, Lyndsey Gott & J. Anderson Thomson, Jr. Antidepressant medication is the most commonly prescribed treatment for people with depression. They are also commonly prescribed for other conditions, including bipolar depression, post-traumatic stress disorder, obsessive-compulsive disorder, chronic pain syndromes, substance abuse and anxiety and eating disorders. According to a 2011 report released by the US Centers for Disease Control and Prevention, about one out of every ten people (11%) over the age of 12 in the US is on antidepressant medications. Between 2005 and 2008, antidepressants were the third most common type of prescription drug taken by people of all ages, and they were the most frequently used medication by people between the ages of 18 and 44. In other words, millions of people are prescribed antidepressants and are affected by them each year. The conventional wisdom is that antidepressant medications are effective and safe. However, the scientific literature shows that the conventional wisdom is flawed. While all prescription medications have side effects, antidepressant medications appear to do more harm than good as treatments for depression. We reviewed this evidence in a recent article published in the journal Frontiers in Psychology (freely available here). The widespread use of antidepressants is a serious public health problem, and it raises a number of ethical and legal issues for prescribers (physicians, nurse practitioners). Here, we summarize some of the most important points that prescribers should ethically tell their patients before they prescribe antidepressant medications. We also discuss the ways that prescribers could be held legally liable for prescribing antidepressants. Finally, we implore practitioners to update the informed consent procedure for antidepressant medication to reflect current research and exercise greater caution in the prescription of antidepressants.
How antidepressant medication works
Most antidepressants are designed to alter mechanisms regulating serotonin, an evolutionarily ancient biochemical found throughout the brain and the rest of the body. In the brain, serotonin acts as a neurotransmitter—a chemical that controls the firing of neurons (brain cells that regulate how we think, feel, and behave). However, serotonin evolved to regulate many other important processes, including neuronal growth and death, digestion, muscle movement, development, blood clotting, and reproductive function. Antidepressants are most commonly taken orally in pill form. After they enter the bloodstream, they travel throughout the body. Most antidepressants, such as the selective serotonin reuptake inhibitors (SSRIs), are intended to bind to a molecule in the brain called the serotonin transporter that regulates levels of serotonin. When they bind to the transporter, they prevent neurons from reabsorbing serotonin, which causes a buildup of serotonin outside of neurons. In other words, antidepressants alter the balance of serotonin in the brain, increasing the concentration outside of neurons. With long-term antidepressant use, the brain pushes back against these drugs and eventually restores the balance of serotonin outside of the neuron with a number of compensatory changes. It is important to realize that the serotonin transporter is not only found in the brain—it is also found at all the major sites in the body where serotonin is produced and transported, including the gut and blood cells called platelets. Since antidepressants travel throughout the body and bind to the serotonin transporter wherever it is found, they can interfere with the important, diverse processes regulated by serotonin throughout the body. While physicians and their patients are typically only interested in the effects of antidepressants on mood, the harmful effects on other processes in the body (digestion, sexual function, abnormal bleeding, etc.) are perfectly expectable when you consider how these drugs work.
Antidepressants are only moderately effective during treatment and relapse is common Since the brain pushes back against the effects of antidepressants, the ability of these drugs to reduce depressive symptoms is limited (see our article for a review). While there is some debate over precisely how much antidepressants reduce depressive symptoms in the first six to eight weeks of treatment, the consistent finding is that the effect is quite modest.
Many people who have suffered from depression report a substantial symptom-reducing benefit while taking antidepressants. The problem is that symptoms are also substantially reduced when people are given a placebo—a sugar pill that lacks the chemical properties of antidepressant medications. In fact, most of the improvement that takes place during antidepressant treatment (approximately 80%) also takes place with a placebo. Of course, antidepressants are slightly more effective than placebo in reducing symptoms, but this difference is relatively small, which is what we mean when we say that antidepressants have a “modest” ability to reduce depressive symptoms. The pushback of the brain increases over months of antidepressant treatment, and depressive symptoms commonly return (frequently resulting in full blown relapse). Often this compels practitioners to increase the dose or switch the patient to a more powerful drug. Prescribers fail to appreciate that the return of symptoms often occurs because the brain is pushing back against the effect of antidepressants. 3. The risk of relapse is increased after antidepressant medication has been discontinued Another effect of the brain pushing back against antidepressants is that the pushback can cause a relapse when you stop taking the drug. This pushback effect is analogous to the action of a spring. Imagine a spring with one end attached to a wall. An antidepressant suppresses the symptoms of depression in a way that is similar to compressing the spring with your hand. When you stop taking the drug (like taking your hand off the spring from its compressed position), there is a surge in the symptoms of depression (like the overshoot of the spring before it returns to its resting position). The three month risk of relapse for people who took a placebo is about 21%. But the three month risk of relapse after you stop taking an SSRI is 43%—twice the risk. For stronger antidepressants, the three month risk is even higher.
Antidepressants have been found to cause neuronal damage and death in rodents, and they can cause involuntary, repetitive movements in humans.
Antidepressants can kill neurons (see our article for a review). Many medical practitioners will be surprised by this fact because it is widely believed in the medical community that antidepressants promote the growth of new neurons. However, this belief is based on flawed evidence—a point that we address in detail in our article. One way antidepressants could kill neurons is by causing structural damage of the sort often found in Parkinson’s disease. This neurological damage might explain why some people taking antidepressant medication can develop Parkinsonian symptoms and tardive dyskinesia, which is characterized by involuntary and repetitive body movements. Many prescribers mistakenly think these syndromes only occur in patients taking antipsychotic medications.
Antidepressants may increase the risks of breast cancer, but may protect against brain cancers .
Recent research indicates that antidepressants may increase the risk of cancer outside of the brain, such as breast cancer. However, the neuron-killing properties of antidepressants may make them potentially useful as treatments for brain cancers, and current research is testing this possibility.
Antidepressants may cause cognitive decline.
Since neurons are required for proper brain functioning, the neuron-killing effects of antidepressants can be expected to have negative effects on cognition. In rodents, experiments have found that prolonged antidepressant use impairs the ability to learn a variety of tasks. Similar problems may exist in humans. Numerous studies have found that antidepressants impair driving performance, and they may increase the risk of car accidents. Recent research on older women also indicates that prolonged antidepressant use is associated with a 70% increase in the risk of mild cognitive impairment and an increase in the risk of probable dementia. 7.Antidepressants are associated with impaired gastrointestinal functioning The action of antidepressants results in elevated levels of serotonin in the intestinal lining, which is associated with irritable bowel syndrome. Indeed, antidepressants have been found to cause the same symptoms as irritable bowel syndrome—pain, diarrhea, constipation, indigestion, bloating and headache. In a recent study, 14-23% of people taking antidepressants suffered these side effects. 8. Antidepressants cause sexual dysfunction and have adverse effects on sperm quality. Depression commonly causes problems in sexual functioning. However, many antidepressants make the problem worse, impairing sexual desire, arousal, and orgasm. The most widely studied and commonly prescribed antidepressants—Celexa, Effexor, Paxil, Prozac, and Zoloft—have been found to increase the risk of sexual dysfunction by six times or more. Evidence from case studies suggests that antidepressants may also interfere with attachment and romantic love. Some antidepressants have been found to negatively impact sperm structure, volume, and mobility. 9. Antidepressant use is associated with developmental problems Antidepressant medication is frequently prescribed to pregnant and lactating mothers. Since SSRIs can pass through the placental barrier and maternal milk, they can affect fetal and neonatal development. Generally, if SSRIs are taken during pregnancy, there is an increased risk of preterm delivery and low birth weight. Exposure during the first trimester can increase the risk of congenital defects and developing an autism spectrum disorder, such as Asperger’s Syndrome. Third trimester SSRI exposure is associated with an increased risk of persistent pulmonary hypertension in the newborn (10% mortality rate) and medication withdrawal symptoms such as crying, irritability, and convulsions. Prenatal exposure to SSRIs is also associated with an increased risk of respiratory distress, which is the leading cause of death of premature infants. 11\\10. Antidepressant use is associated with an increased risk of abnormal bleeding and stroke Serotonin is crucial to platelet function and promotes blood clotting, which is important when one has a bleeding injury. Patients taking SSRIs and other antidepressants are more likely to have abnormal bleeding problems (for a review see our article). They are more likely to have a hemorrhagic stroke (caused by a ruptured blood vessel in the brain) and be hospitalized for an upper gastrointestinal bleed. The bleeding risks are likely to increase when SSRIs are taken with other medications that reduce clotting, such as aspirin, ibuprofen, or Coumadin . 11. Antidepressants are associated with an increased risk of death in older people. Depression itself is associated with an increased risk of death in older people—primarily due to cardiovascular problems. However, antidepressants make the problem worse. Five recent studies have shown that antidepressant use is associated with an increased risk of death in older people (50 years and older), over and above the risk associated with depression. Four of the studies were published in reputable medical journals—The British Journal of Psychiatry, Archives of Internal Medicine, Plos One, and the British Medical Journal—by different research groups. The fifth study was presented this year at the American Thoracic Society conference in San Francisco. In these studies, the estimated risk of death was substantial. For instance, in the Women’s Health Initiative study, antidepressant drugs were estimated to cause about five deaths out of a 1000 people over a year’s time. This is the same study that previously identified the dangers of hormonal replacement therapy for postmenopausal women. In the study published in the British Medical Journal, antidepressants were estimated to cause 10 to 44 deaths out of a 1000 people over a year, depending on the type of antidepressant. In comparison, the painkiller Vioxx was taken off the market in the face of evidence that it caused 7 cardiac events out of 1000 people over a year. Since cardiac events are not necessarily fatal, the number of deaths estimated to be caused by antidepressants is arguably of much greater concern. An important caveat is that these studies were not placebo-controlled experiments in which depressed participants were randomly assigned to placebo or antidepressant treatment. For this reason, one potential problem is that perhaps the people who were taking antidepressants were more likely to die because they had more severe depression. However, the paper published in the British Medical Journal was able to rule out that possibility because they controlled for the pre-medication level of depressive symptoms. In other words, even among people who had similar levels of depression without medication, the subsequent use of antidepressant medications was associated with a higher risk of death. These studies were limited to older men and women. But many people start taking antidepressants in adolescence or young adulthood. Moreover, since the risk of a relapse is often increased when one attempts to go off an antidepressant (see point 3 above), people may remain on medication for years or decades. Unfortunately, we have no idea how the cumulative impact of taking antidepressants for such a long time affects the expected lifespan. In principle, long-term antidepressant use could shave off years of life. It is commonly argued that antidepressants are needed to prevent depressed patients from committing suicide. Yet there is a well-known controversy over whether antidepressants promote suicidal behavior. Consequently, it is not possible to reach any firm conclusions about how antidepressants affect the risk of suicidal behavior. However, most deaths attributed to antidepressants are not suicides. In other words, antidepressants appear to increase the risk of death regardless of their effects on suicidal behavior. We suggest that antidepressants increase the risk of death by degrading the overall functioning of the body. This is suggested by the fact that antidepressants have adverse effects on every major process in the body regulated by serotonin. 12. Antidepressants have many negative effects on older people Most of the research on the adverse health effects of antidepressants has been conducted on older patients. Consequently, our conclusions are strongest for this age group. In addition to cognitive decline, stroke and death, antidepressant use in older people is associated with an increased risk of falling and bone fracture. Older people taking SSRIs are also at an increased risk of developing hyponatremia (low sodium in the blood plasma). This condition is characterized by nausea, headache, lethargy, muscle cramps and disorientation. In severe cases, hyponatremia can cause seizures, coma, respiratory arrest and death. The fact that most research has been conducted on older people does not mean that antidepressants do not have harmful effects on the young. As previously discussed, antidepressants can have harmful effects on development. Moreover, many people start taking these drugs when they are young and remain on them for years or decades. In principle, the negative effects of these drugs could be substantial over such long periods of time. Altogether, the evidence leads us to conclude that antidepressants generally do more harm than good as treatments for depression. On the benefit side, the drugs have a limited ability to reduce symptoms. On the cost side, there is a significant and unappreciated list of negative health effects because these drugs affect all the processes regulated by serotonin throughout the body. While the negative effects are unintended by the physician and the patient, they are perfectly expectable once you understand how these drugs work. Taken together, the evidence suggests that these drugs degrade the overall functioning of the body. It is difficult to argue that a drug that increases the risk of death is generally helping people. There may be conditions other than depression where antidepressants are generally beneficial (e.g., as treatments for brain tumors and facilitating recovery after a stroke), but further research in these areas is needed (see our article). Ethical and Legal Issues Physicians and other medical practitioners have an ethical obligation to avoid causing greater harm to their patients. The Latin phrase primum non nocere (“first, do no harm”) that all medical students are taught means that it may be better to do nothing than to risk causing a greater harm to a patient. Although all prescription medications have adverse side effects that can cause harm, practitioners have an ethical obligation to not prescribe medications that do more harm than good. The evidence we have reviewed suggests practitioners should exercise much greater caution in the prescription of antidepressants and to reconsider their use as a first line of treatment for depression. Additionally, we suggest that physicians and other medical practitioners should consider their potential legal liability. Legal liability for prescribing antidepressants Medical practitioners can be sued for prescribing antidepressant medications if doing so violates their state’s standard of care laws. In most states, the standard of care is what a “reasonably prudent” practitioner in the same or similar field would do. The standard of practice is not defined by what the majority of physicians do because it is possible for an entire field to be negligent. Since studies on the health risks associated with antidepressant use (e.g., stroke, death) have been published in well-respected medical journals, medical practitioners could possibly be vulnerable to malpractice lawsuits. For instance, it seems likely that a reasonably prudent physician should be aware of the medical literature and avoid prescribing medications that could increase the risk of stroke and death. Prescribers can also be held liable for not discussing information about medical risks so that patients can give informed consent for medical treatments and procedures. Prescribers have a duty to discuss the benefits and risks of any recommended treatment. Consequently, medical practitioners should discuss with their patients that antidepressant medication is only modestly more effective than placebo and could increase the risk of neurological damage, attentional impairments, gastrointestinal problems, sexual difficulties, abnormal bleeding, cognitive impairment, dementia, stroke, death, and the risk of relapse after discontinuation. Antidepressants must cause harm to create liability A medical malpractice lawsuit can only succeed if the antidepressant caused harm to the patient. It is important to realize that the antidepressant does not need to be the only cause of the harm—it only needs to contribute to or exacerbate the harm. As we have argued, antidepressants play a causal role in many adverse health outcomes because they disrupt serotonin, which regulates so many important processes throughout the body. This may make it particularly difficult for a medical practitioner to defend against a medical malpractice suit from a patient who experiences any of a number of adverse health effects while taking an antidepressant. For instance, if a patient has a stroke while taking an antidepressant, the evidence that antidepressants increase the risk of stroke suggests that the antidepressant may have contributed to the patient’s stroke, even if it was not the only cause. Conclusion The evidence now indicates that antidepressants are less effective and more toxic than commonly believed. From ethical, health, and legal perspectives, it seems prudent for individual practitioners and professional medical organizations to revise informed consent guidelines and reconsider the status of antidepressants in standards of care for many diagnoses and as the front line treatment for depression. With older people, for instance, the current data suggest informed consent must include a discussion of the increased risk of hemorrhagic stroke and even early death. We suspect that if prescribers realized they were placing themselves at legal risk for failing to discuss the adverse health effects of antidepressants with their patients, not only would they be more likely to discuss such information, they would be less likely to recommend these drugs in the first place. Paul W. Andrews is an assistant professor in the Department of Psychology, Neuroscience & Behaviour at McMaster University in Canada. He has a PhD in Biology from the University of New Mexico and a law degree from the University of Illinois at Urbana-Champaign. His work on the evolution of depression with J. Anderson Thomson, Jr. has been featured in the New York Times Sunday Magazine and Scientific American Mind. Taken with respect and gratitude. directly from ANNECWOODLEN’s Blog BEHIND THE LOCKED DOORS OF INPATIENTS PSYCHIATRY. http://behindthelockeddoors.wordpress.com/2014/01/12/you-and-your-antidepressant-2/
and they really work for you, then don’t listen to me, keep taking them and the more power to you.
Do you work at a job and earn a living while you take anti-psychotic drugs? Do you support a family or take care of one while your wage-earner partner can keep her or his job without worrying about your sanity? Good, then the “anti-psychotic” pills you take (or I’ll add in for good measure, god help us all, the “anti-depressant” pills) are doing what we were always told they were supposed to do. Or if you don’t work or care for a family, if not, do you at least live a fulfilling single’s life, with good capable friends and family and a worthwhile occupying activity that keeps your mind free of craziness and despondency the preponderance of the time? Terrific!Then those pills, whether they be antipsychotic or anti-depressant pills actually function and you are one lucky dude or chick. I say to you, whoever you are, All Cheers and GO FOR IT! Please do not worry about anything further I say in this or any other blog post. Whatever I write from here on in, whatever I say that you do not agree with, IT IS NOT INTENDED FOR YOU. Why? Because by your report, YOUR PILLS WORK and they do a bloody good job of it. So who’s to tell you to change anything? You have no complaints and aside from the possibility that your brain might sustain a little shrinkage, if research about such things proves correct, you have nothing to worry about. In truth, most aging brains shrink and sustain bits of damage along the way. Lots of things can happen…most of them not drug related at all. One simply cannot worry about a “what if” future, when the present is so bright.
So I repeat, IF you happen to be one of those lucky ones I have described and actually have no complaints, IF, better than that, if you find that your anti-psychotic drug or anti-depressant pills work terrifically well, you have had no relapses, suffer no terrible trade-offs in terms of side effects, then stop reading this blog post right this minute. Why? Because I have nothing to offer you and nothing to say to you. Okay? You don’t need me, and you won’t want to hear what I am going to say to the others of us out there whose experience has been somewhat to radically different.
But this is a SHOUT OUT to you, there, who don’t like your drugs and don’t want to take them. Or find them minimally helpful, or wonder frankly whether they really do any of what the docs tell you they do, forewarned is forearmed…This post is going to be about the charade of anti-psychotic drugs, for the most part, about the fact that they do not in fact function in the anti-schizophrenia fashion that you have been told. (I likely won’t have the time or energy at this point, being on AP drugs myself, to get into the appalling farce of what are called anti-depressants…You could turn to MAD IN AMERICA by Robert Whitaker for a take on those — just check out his chapter on Prozac for a taste…) It isn’t that AP drugs do nothing at all. They do attack the brain’s neurotransmitter levels, in some fashion or another. And not just the vaunted dopamine and or serotonin levels either. No, most atypical antipsychotic drugs have effects on histamine, glutamine, noradrenaline and acetylcholine and likely a whole host of other brain chemicals we haven’t even scratched the surface of, in the sense of knowing their function in the brain, or in any part of the brain for that matter.
Do you know, did you know, that the Dopamine Hypothesis, the fundmental reason why there are antipsychotic drugs out there now in so many burgeoning numbers was always bogus? It never held water, ever. There was NEVER any reason to believe that dopamine caused schizophrenia, or that a dyspfucntional level of dopamine lay behind the majority of schizophrenic symptoms. It was a bold-faced and bald-pated lie, that’s because it is as old as the hills and as tiring. You don’t have schizophrenia the way one has diabetes, because you have a chemical imbalance in your neurotrnamitters that these neat little AP drugs resolve and rebalance. Sorry, folks, but that has been baloney ever since we all started developing parkinsonism and KNEW, just KNEW that something was terribly wrong with these miracle drugs that made us feel so terrible.
Did you know that it used to be the criteria for a true neuroleptic, the only way they knew they had a functioning adequate drug, was because it successfully induced parkinsonism in patients. That is, if it induced adequate BRAIN DAMAGE, then they knew it would “work” against schizophrenia. Because the theory was, both in ECT and insulin coma, as it was in early AP drugs like Thorazine and Haldol that you had to induce brain damage to get a therapeutic effect in the illness. Crazy no? No, not at all, not when you stood to make ZILLIONS and Gazilliions of dollars on these drugs. Not only could you treat a hospialized crazy person with these drugs, and make them “better” and push them out of the hospital, but you could set up a plan for future care, AFTER CARE, that specified that JUST like diabetes, a person had to keep taking these drugs. You never just recovered from an illness like schizophrenia, no. The drugs were miracles yes, but not like antibiotics, They never cured you. they just were a treatment that you had to keep taking. The Gift that keeps on giving…at least for the Pharmaceutical companies who dreamed up the protocol. If they could get a person onto the AP drugs, once, and mandate legally or via a persuasive mental health system that the patient stay on them for life, well then, what a system, and what a money maker!
Oh my eye! What a load of hog wash. All they ever did was dream up neuroleptic (“brain seizing”) drugs that physically subdued people and made them more amenable to nursing. So the hospital nurses could be more nursey nursey and kinder, and more kindly disposed to patients who were now drooling and dulled and seemed much genuinely sick, and the patients could be seen as more ill and less hostile and unpleasant to be around, less difficult to treat qua patients..
But it was a strange transformation, because the more sick the patients were made by taking these neuroleptic drugs, the less they were treated like the troubled and suffering PEOPLE they were to begin with. Once a patient, they assumed that role, and the whole cycle began and has never stopped to this day. “Schizophrenia is an illness just like diabetes.” That was the canard I was told in 1980 — we are still being handed the same disgusting lie! — when I was first officially diagnosed with the condition, or told the name to my face at any rate. “You’ll never recover, and you will likely have relapses, but you won’t be a back wards patient if you take these pills like a good girl, and do as I tell you. No schizophrenia isn’t a death sentence these days but it IS a life sentence…” So what did I do? I swallowed my 500mg of Melleril, yes i did, and I told the doctor I was feeling much better, yes I did. Because frankly I didn’t know how I felt and I felt OBLIGED to tell the doctor what he wanted to hear. How else was I going to get out of the hospital and get off those horrible pills that made me put on 20 pounds in three weeks and made me feel so dull and sluggish and tired all the time? Besides, how could I possibly, in those conditions, KNOW how I felt, when the nurses themsevlves colluded to tell me how much better I looked and was doing? I knew I couldn’t read or think for myself any longer. But they told me that that was my negative symptoms and had nothing to do with the drugs. It was a problem I would have to come to terms with by talking with a therapist…which was a good thing, that they suggested I see a therapist. Back in those days, it was often frowned upon that ANYONE with schizophrenia actually do any talking to anyone at all. After all, if you talked about yourself or your illness, you might upset yourself or the whole applecart…You might actually go crazy again, you were that UNSTABLE! No talk therapy was usually frowned upon for “schizophrenics.” It was seen as not good for them, and destabilizing. What we needed was daily meds and mouth checks and maybe day treatment with a hours job to do each day, like capping test tubes for the lab to keep us busy. Lucky was he or she who could function as a bus boy or table setter. Most of us barely made it to day treatment on time, before sacking out on a couch somewhere for a long snooze to let the morning’s dose of thorazine 1000mg or Melleril 800mg wear off a little before coffee hour or lunch time.
Some of us actually turned blue on high doses of Chlorpromazine, and she eventually died, at the age of 28. There was a lot of relapses and some suicides, but NO ONE actually went out and got a job and quit the hospital and got better. No, because the whole damned system was set up in such a way that once you were set up on anti-psychotic drugs, with a diagnosis of schizophrenia, you were put on social security disability payments for life,..and drugs for life followed, and the trap ensued that meant your whole life was a rolling down hill of poverty and more drug taking and relapses…until maybe something amazing happened to get you out of the systematic rut the psychiatric system had placed you in.
MAYBE you found someone you fell in love with, someone who not only would take care of you, but who hated to see you dull and passionless and sexless on the drugs and encouraged you to SLOWLY wean yourself off of them. And maybe it happened to a few of us that it was a success, because love can really conquer all, even the notion that schizophrenia is a life-long hopeless illness. If you got off the drugs in the right way, slowly, and stopped seeing the doctor who told you you would definitely relapse, maybe just maybe you didn’t. Maybe your sex life came back and you found out it was better than Haldol and thorazine, and better than being dulled by the system’s poverty and being sick. And once in a while that person’s husband was so loving and encouraging that they got married and moved away and she stayed well enough to take up a hobby that turned out to make a little money by itself. So she turned it into a business, and miracle of miracles, she didn’t fall into the trap of SSDI after all but stayed well without the AP drugs and became a businesswoman without enough time to think about being schizophrenic again…
But alas, that didn’t happen very often. Not nearly often enough. There were far too many tragedies compared to the rare success story. Too many people getting diagnosed with schizopohrenia, and then when the fads for multiple personality disorder came, with that, and all the other fads that had to happen because the drug companies had drugs that they needed to sell use on people and they had to have diagnosese to fit the pharmaceutical picture so they could sell the drugs they had on hand. ADHD, autism are only the latest two…
But I digress, I digress, so let me tell me my own story, if I have the time and energy.
I got sucked in. I did. I was hospitalized in 1980, and even before them. But in 1980, as far as I can now recall, I was up late at night, for the third night, in the hospital kitchenette in an absolute sweating panic about my hands. Why? Because I had this strong delusional belief that they were not my own, but that my twin sister had taken them over and controlled them. I could feel them, and in a sense I could see this process happening. And I heard voices telling me that I was in danger. A nurse came in, and asked me why I was up, and in a panic, i told her. I said, somethings wrong with my hands! They aren’t mind, my sister has control of them! And I can’t sleep, I can’t sleep!
Now, the nurse was a kind woman and I think she meant to help, but she couldnt do anything for me but tell me she would call the doctor, who came, in his fashion, running. I was sweating bullets by then, sitting at the empty lunch table, mumbling about my sister and my stolen hands. What could he do, given his own pharma-company training, but offer me some drug assistance and promise me that it would help, that it was what I “needed” in the throes of my illness?
I believed him, I did. And when he came back the next morning, after I had been dosed three times that night with increasing amounts of Melleril until I finally slept, he pronounced that I suffered from the mental version of diabetes. schizophrenia…The rest, well, if it isn’t everyone’s history, it is a version of it. And it involves SSDI and even SSI because I had never been able to work a full time job even before then. And none of the many drugs I took after that ever did anything for me but disable me more than before. And I would stop them and be hospitalized again with what they now suspect is withdrawal psychosis, or could have been. And I would be started back on the drugs, or a long-acting injection that was supposed to prevent hospitalization. It never did much good…I was a basket case, a basket case. I never washed or changed my clothing, or even took off my shoes, not even to go to bed. NO I wore those hiking boots for a good year and a half before they even saw me take off the socks I wore underneath them…
So how much did the AP drugs help me? And when they started to restrain me for paranoid fears and trying to escape a locked unit, did I then say Enough is enough, you cannot torture me, I have schizophrenia? No, I accepted mechanical restraints for three days at a ttime as a form of treatment. One doctor actually told me that schizophrenics don’t respond badly to being tied to a bed for a long time, it helps them, he said, by reducing stimulation…So they did that, and they kept me in seclusion for weeks at a time…until finally I would cry Uncle and take the drug they wanted me on, and go home again, prepared for the next certain relapse, because what else was there….I had a life, yes, but it wasn’t much. It was just hospitals and restraints and drugs that never helped me and cruelty from nurses that didn’t know they were hurting me. And doctors who were damaging me without thinking twice about it. And I didn’t even have the mental wherewithal to know that the drugs were the prime offenders. The PRIME offenders.
It is now 5:30am and I have been up all night. My shoulder hurts, from where i have a slightly torn rotator cuff and frozen shoulder tendonitis… I don’t have a bed, only a recliner I should not sleep in…I am a mess, and I am also NOT going to continue to take my Abilify and Geodon much longer…I cannot. I cannot. I do not know what will happen, but I am too afraid of what will happen if I take it, to take them, though I have never felt they did me more harm than good. I just don;t know what real GOOD they do me.
More later, or on another day. Sorry this was so impassioned.
This is an incredible video, which, though long, is well worth watching. For anyone who believes that recovery without medications is impossible or not likely, you should watch this with at least half an open mind. And for anyone who has given up hope, this should give you a lot of hope. I usually cannot watch entire videos half this long, but I watched this one all the way through, even though I admit I had to take breaks because (Yes, I take meds myself) my attention span is short…But it was worth it to learn that one of the women featured not only recovered from her severe schizophrenia without taking psychiatric medication, she remained absolutely psychosis free and became a psychiatric nurse for 30 years. What I would give to speak to her about the sorts of treatment, or abuse that passes for treatment here in CT! But be that as it may, do watch this if you can. It is absolutely astonishing. And beautiful too.
15 minutes no longer, and much of it was scrambling to photograph this before I gave it to the person…I heard her friends laughing about “what is that on her back…OH its her hoodie!” but what did I care? I know I can draw, and i only had a few minutes, with all of them squirming around and changing positions…They have NO idea how hard it is to draw someone in action!
The next one is a work in progress, about four point restraints and abject terror, if I can accomplish what I want to do in my usual pencil painting… SO far so good, but we will see.
This will be a picture of four point restraints, or wrist restraints coupled with an expression of abject horror, and more…If I can accomplish it with my usual pencil painting. Right now, alas, the hands looks a little more like marionette type hands than really shackled though the restraints are drawn exquisitely accurately.
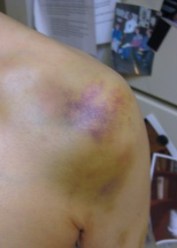
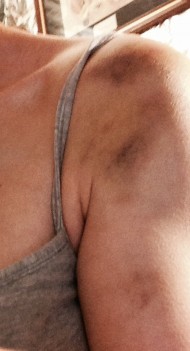
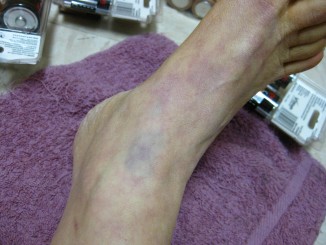
I am uploading my new PAD, IN ORDER TO AVOID INJURIES SUCH AS THESE, brought on in Jan 2013 at Hartford Hospital’s Institute of Living. and photographed the very day I was released.
Now I have a torn left rotator cuff..anything to do with this, I wonder? from IOL 4 point restraintsLeft shoulder,,, caused by brutality or four point restraints at IOLBruises on bare ankle from long term use of 4-point leather restraint cuffs, locked so tightly i could not move. — from IOL 2013
Although I brought the PAD both to the Institute of Living in Jan 2013 and to Yale in Aug 2013, I don’t know what happened that it was abrogated so deeply and so widely. At Yale, they forced medication on me, holding me down three times daily at times, resulting in such psychic regression that as you have all read, I routinely stripped naked, defecated on the floor and smeared feces all over the wall. That I was at one and the same time attempting to communicate with these people, by WRITING WORDS IN MY SHIT, was utterly disregarded by all at the time. But I assure you that if I was regressed and psychotic in doing such things, I was nevertheless still verbal! I am also virtually certain that had they not grabbed me, pinned me to the floor and held me down for three painful injections in the buttocks of a drug that Soviet dissidents have long called pure torture (Haldol in the 60s/70s was the subject of many a televised congressional hearing, and discussed in just such terms…) my response would have been very very diffferent indeed.
That said, they did what they claimed they had to do, and when I left, I left feeling absolutely convinced that my life was and had been mortally threatened, that I could NEVER return, that I would literally be murdered if ever I dared. Nothing more need be said about such sadistic places as the Institute of Living at Hartford Hospital. Even in the Patient Care Guide and Journal, they are at pains to make it clear that any loud or out of control behavior will be dealt with swiftly and severely, with seclusion, restraints, and even charges pressed by the local authorities! (NO attempts to soothe the traumatized patient or act on what CMS has urged be the best practices of trauma-informed and patient-centered-care at the IOL. No, at Hartford Hospital, it is all about NO SWEARING and staying quiet, non-disruptive. The “Or else” threat behind it all is not even implied but openly stated in their rules and obligations section. Why ANYONE would want to set themselves up for treatment in such a place is beyond me…They have even edited out any attempts at kindness from the old handbook that I was given just a year ago. Yale at least attempted to live up to a policy of Trauma-informed and Patient-centered care. When they said No Restraints policy, I believe they meant it, at least in terms of NO MECHANICAL leather and shackles restraints.
And I believe that had Robert Ostroff MD, NOT been in charge of my care during the week or two that Robert Milstein MD was away, some of the brutality might not have occurred at Yale and I might be writing less devastated things about the Washington Square 2 unit, a place I had once so hopefully described as a “soft, gentle place to land in a psychiatric crisis.” But as much as because of my outrageous and disruptive behavior in response to their trauma as because of their repetitive violence and cruelty, I can never return there…a sad thing I suppose, since there is literally no safe place in Connecticut for me.* *more on this later or in another post. What I have posted here is an update in order to Keep me OUT of the hospital as much as to direct my care if I am put inside, It is not the whole thing, only the first two or three pages, I would be happy to upload the whole thing so you can see how I did it, if anyone indicates interest. Let me know. So far it was always the first three pages that got people’s attention. ______________________________________________________
Pamela Wagner’s
PSYCHIATRIC ADVANCE DIRECTIVE 2014
FOR WHEN I AM HOSPITALIZED OR INFORMATION TO HELP TO AVOID IT
Miss Wagner has experienced multiple episodes of severe psychological and physical trauma, including date rape, the suicide of two friends, and domestic abuse by caregivers. She should NOT be subjected to restraints, involuntary seclusion, or forced medication. The use of these inevitably leads to re-traumatizing and injury, regression and severe worsening of her psychiatric symptoms.
HOW TO INTERVENE IN A CRISIS:
DE-ESCALATION IS ESSENTIAL
DO NOT TOUCH ME OR GRAB ME.
DO NOT LAUGH AT ME.
I WILL CALM DOWN IF YOU REMEMBER THAT:
I AM SCARED AND PARANOID.I ONLY FIGHT IF I FEEL UNDER ATTACK. DO NOT USE A SHOW OF FORCE, AS THIS WILL FRIGHTEN ME MORE.
DON’T ISSUE ULTIMATUMS…That will push us all into a corner and serve nothing
AN UNRUFFLED PERSON SHOULD ASK ME TO TAKE A DEEP BREATH, and try other verbal calming techniques. I am always grateful for people remaining calm when I am upset.
NEVER LEAVE ME ALONE IN A BARREN (seclusion) ROOM.
A WEIGHTED OR WARMED-UP BLANKET SOOTHES ME. SOMETHING ICY TO EAT CAN ALSO HELP.
PLEASE LISTEN TO WHAT I HAVE TO SAY. Medication may not be needed if you hear what the problem is.
IF NECESSARY, YOU MAY PERSUADE ME TO TAKE ORAL MEDICATION, if you negotiate this with dignity and kindness. Keep speaking to me calmly and explain your reasoning.
*I cannot reiterate enough that if you utilize 4-point restraints or seclusion, it is virtually guaranteed that you will see regression, increased hostility and aggressiveness as a result. Please don’t do something everyone will regret.
ADDITIONAL STATEMENT TO CAREGIVERS (PLEASE READ)
It is important that you understand that I do not have a personality disorder (you can confirm this with Dr Angela C——, or any of my longtime outpatient providers and friends and family members). If my behavior/emotions seem out of control, it is because I am out of control – temporarily.
I have had tertiary CNS Lyme disease, which I was informed after multiple positive PCR and Western Blots during treatment was likely incurable. During my initial illness, my brain developed MRI lesions which may predispose me to temporary emotional and behavioral abnormalities but these are NOT my norm. Anyone who knows me well would tell you that, if you ask them.
I am not always able to communicate my fear but because I feel so threatened and unable to communicate clearly about it (lest there be consequences to me) I may become very angry at the hospital situation. I am not an angry person, but I do have trauma issues, as many people do.
Please be aware that I am sometimes mute, in frustration and overwhelmed by circumstances. You can provide me with a pad and pen to facilitate communication, but berating me into speaking will no purpose and may only precipitate anger.
Ascertain from me whether the information you have at hand is correct. Too many records and hospital charts have been drawn up on faulty information from earlier charts or information gleaned from others but not from me, and the consequences to my treatment have been devastating.
I would prefer NOT to take any medications and will resist them. I want to experience my LIFE AND MY FEELINGS. If you insist on meds, the ones that work best are _______.
I will not take any drug that induces weight gain. If you force it, know that I will fight you, tooth and nail.
And now I highly recommend that if you want to see the two art pieces of mine that Kayla chose, as well as another poem, go on over to the website and sign up for a digital copy of the magazine. Also because there are some other wonderful pieces of work there too. I was amazed. Some of them moved me to tears…
Hey, we all dream, don’t we? And this is really a remarkable undertaking. Beautifully done both in art and writing (and I would say that whether or not my art and poems were represented…).
Dear Harold Schwartz, Director of the Institute of Living at Hartford Hospital
I believe that I was profoundly harmed by the treatment I received in 2013 on Donnelly 2 South at the Institute of Living at Hartford Hospital, and that what the staff did to me was not only unethical and cruel but that it crossed the line into illegality from the very first. Psychiatric patient abuse is a pattern in Connecticut hospitals, but it was most egregious at the Institute of Living because the staff told me that they knew what they were doing was wrong but that they would get away with it anyway.
That I know I was a difficult patient never justified staff behavior towards me. I was loud and upset and hard for them to deal with, yes. That is precisely why my Psychiatric Advance Directive (PAD) was written out the way it was, and why I made my medical and psychiatric history online so available. When ill, I am frightened and paranoid, which makes me easily roused to irritability and hostility. I know this, from a distance as it were. But knowing this now does not mean I was in control of my emotions. I am by nature neither temperamental nor prone to temper eruptions or throwing things. In addition, I am extremely modest, hardly one to disrobe or urinate in public. My friends and family have at times variously labeled me “stoic” and “peacemaker,” which should tell you a lot. But that I disrobed and urinated on the floor on Donnelly 2 South both horrifies me and concerns me because these behaviors point to something going on distinct from my psychosis: they point to my having been subject to abuse and trauma at the hospital itself.
Let me make it very clear that if I have behaved in such ways before it was only in response to similar extreme circumstances – as when i was subjected over and over to restraints and seclusion in a horrific and sadistic fashion at Manchester Hospital in 2009 and similarly at Middlesex Hospital in 2010. It is too bad that when Sanjay Banerjee MD and Amy Taylor MD took it upon themselves to violate my HIPAA privacy rights and investigate my previous admissions, without my permission (which I expressly refused to grant) they failed to make the connection between the abuse, and my subsequent behaviors…It turns out all they drew as a conclusion was that if those hospitals could use restraints and seclusion ad libitum, so could they. It didn’t seem to matter to Dr Taylor in particular that in 2009 and 2010 measures such as seclusion and restraints not only didn’t work, they made things worse. Not surprisingly, when Dr Taylor followed these examples I regressed completely, just as my PAD predicted.
I was admitted to Donnelly 2 South, and I came in with a very detailed Psychiatric Advanced Directive as I said. I made it very clear that my online electronic medical record was also available. It included documents such as my narcolepsy diagnostic consult and special documentation assessing my need for a higher than usual dosage of Ritalin, written by my former sleep specialist, Mary B O’Malley, MD PHD who was also my psychiatrist from 2000-2009. Included as well was a letter she wrote to my present psychiatrist, Dr Angela Cappiello, explicitly stating her conviction that I do not have a personality disorder, NOS, borderline traits, or otherwise.
According to Dr. Sanjay Banerjee he read every page of these documents. That is what he told me. He even praised me, saying he wished every patient would come so prepared. Moreover, when he spoke with Dr. Cappiello, he brushed off my concerns about anyone misperceiving me as having a personality disorder. My brother, Philip Spiro, MD, himself a psychiatrist, brought up the same matter when in discussion with Laurie Denenberg, LCSW, but her response was much the same: “Personality disorders are not a part of the picture here. We intend to honor her PAD. We are glad that she has had the foresight to prepare such a document.”
If this was so, then how did it come to pass that Amy Taylor, MD wrote on my history and discharge summary that I have a “long history of Borderline personality disorder” and herself diagnosed “Personality disorder NOS with borderline traits”? I was being treated for four weeks for an active psychotic disorder Axis 1. In any event, she could have no way of knowing whether or not I had a personality disorder, given an active an Axis I diagnosis.
On or around February 4, 2013, I walked in frustration away from the quiet room where I had been held captive for nearly three weeks, strolled down the hall, looked out the window and slowly retraced my steps back to the quiet room, which I had been expressly told was NOT a seclusion room (the definition at Hartford Hospital’s Institute of Living of a seclusion room is a “room to which the door is locked.”) But when I arrived I was confronted by a cohort of staff who proceeded to 4-point restrain me to the bed, even though I was quiet and put up no resistance. Not wanting to give them any reason or justification, I passively lay down on the bed and placed my own limbs out for the restraint cuffs, saying, (I quote my journal entry made later that evening): “For shame. You ought to be ashamed of yourselves. I am not and never was a danger to myself or others.” Their response was “ You refuse to follow directions so we do not know what you will do. This is not punishment, Pamela, this is what your behavior brings on every time.”
From that point on, the threshold for restraints was extremely low. They always restrained me, spread-eagled, so tightly I couldn’t move a muscle. They never permitted bathroom breaks or even used a bedpan, instead they made me defecate in my clothing. They never even let my hands free to eat. I would fall asleep rapidly after three routine punishment needles in the buttocks: Haldol, Ativan and Benadryl—whether I just had my regular meds or not, and they would invent reasons to maintain me in restraints even after I had been asleep for hours. When I woke, groggy and hardly dangerous to anyone, they would grill me with questions that I could not answer. They would then use my inability to respond as reason not to let me out, even when I asked, as the chart recorded, in a “soft sedated voice” for release. They would re-inject me, to put me back to sleep instead.
In the evening on Jan 5th, for the second time that day, they brutally restrained me for throwing half a graham cracker at the wall. Then, as usual, they left me like that for six hours, even after I fell asleep. But in point of fact, though, I could never earn my way to release from restraints by good behavior or quietly, calmly asking for release. I had never done anything to earn my way into them in the first place. I was never violent until they threatened me. They refused to release me until I literally cried, “Uncle” when they told me to.
As to those vaunted “shows of force” what did they expect? Presented with a cohort of threatening staff personnel I saw one thing: an impending assault. I know they anticipated my panic; they said as much in my chart. Isn’t that the point of a planned “show of force” – to induce fear and panic? Why else do it? So why should it be any surprise, when I defended myself when they forcibly, physically grabbed me? When they stuffed me into a body bag and were trying to tighten the straps, surely you can understand why anyone would bite the hand of an attacker whose digits came near the face. I had done nothing but refuse to enter the body bag willingly. I simply was passive. I did not fight or resist until they grabbed my body and assaulted me.
But none of it should have happened. My Advanced Directive explained in exquisite detail exactly what to do and what I respond to better than fear tactics and force. In fact, It is beyond me, knowing that one of the admission diagnoses I came in with was PTSD, how anyone could possibly approve in advance, permission to use restraints and seclusion “just in case they are needed”. Why not counsel the person asking for this advance “right to restrain” to do all in his power not to restrain me and to work with the PAD instead?
Here’s what SAMHSA the substance abuse and mental health services administration publication has to say on seclusion and trauma:
“Studies suggest that restraints and seclusion can be harmful and is often re-traumatizing for an individual who has suffered previous trauma…
“Further, there is a common misconception that seclusion and restraint are used only when absolutely necessary as crisis response techniques. In fact, seclusion and restraint are most commonly used to address loud, disruptive, noncompliant behavior and generally originate from a power struggle between consumer and staff. The decision to apply seclusion or restraint techniques is often arbitrary, idiosyncratic, and generally avoidable.
“Moreover, some studies indicate that seclusion and restraint use leads to an increase in the behaviors that staff members are attempting to control or eliminate.
I have been traumatized, and not just by hospitals. I was date-raped three times in my twenties and experienced traumatic domestic abuse by a long-term roommate. The cover sheet on the PAD made very clear that due to these trauma issues, I could not tolerate being secluded or restrained without serious consequences: regression and serious worsening of symptoms. Unfortunately, as soon as the staff saw fit to use physical methods of coercion and control on me from the first time a staff member grabbed me and pushed me with his lower torso, I ceased improving, and my symptoms went downhill. Did they really think they were being kind and compassionate?
Staff violence begets violence….
I tried to get help even when on the unit, at least I tried when I was free to, to make calls or leave my seclusion… that is to say, forced three -week-long stay in the quiet room last winter. I made many calls to the hospital’s patient advocate office, but the sole time anyone made contact was when the advocate came to hand me some paperwork – I believe I was actually in 4-point restraints at the time — papers I could not read about the forced medication hearing. I needed her advocacy, but she never responded to my panicked calls in any way that was helpful to me. I wanted her help, but she never came by to ask me what I needed. She was less than useful, the fact that I had to go through her, essentially a hospital employee, and her refusal to respond, contributed to my ongoing panic and desperate feelings of aloneness and depression. No wonder Dr. Sanjay Banerjee attempted to force ECT on me, without any prior discussion of it with me whatsoever.
And where did the ECT discussion come from? My PAD states in no uncertain terms that I will refuse ECT under any and every circumstance. My brother would be my conservator if Banerjee had sought to go down that road, and he would never have made any decision to counter my wishes on that subject. If Banerjee really read my PAD, he would have known that. I have already had FORCED ECT and it traumatized me terribly. Also it failed to work.
Banerjee had stopped my 75mg of the antidepressant Zoloft during the first or second week I was there. “Do you really need that?” he had asked, “You don’t seem depressed to me.” Obedient, and in any event glad to get off any medication at any time, I shook my head, assenting to the change. A week later, instead of reinstating the Zoloft, Banerjee blamed my sudden “depression” on my refusal of the anti-seizure medication, Lamictal, a drug I had not taken in 6 months. Now he was applying to force me to take ECT, something I was terrified of, and to have calculated brain damageIt was this threat, and the brutality with which the decision was handed down, that started the downhill course of my IOL stay.
The very next weekday, all hell broke loose. When I entered the conference room, I pushed some important notes across the table that I wanted Dr Banerjee and Laurie Dennenberg to read. They refused, claiming that I threw the papers at them. Instead, Dr Banerjee proceeded to berate me, and told me how he had consulted with other hospitals and providers and had read my records against my instructions and Advance Directive, thus violating my HIPAA rights. Moreover, he threatened me with a behavioral treatment plan that would not permit me to do art or writing unless I “behaved.”
I hit the roof, telling him I would sue the hospital and complain to JCAHO, then summarily left, slamming the door, an act that stemmed from feelings of utter impotence, because I couldn’t actually say in words anything more effective.
It could have ended there. I could have been left alone, to cool down and calm myself. But, no, Dr Banerjee had to write for stat meds again, and even though I was on the phone and trying to find someone to talk to, to calm myself, I had to be physically dragged off the chair I sat on, away from the phone and brought to the floor in a physical struggle (because they had attacked first, i.e. physically grabbed me, I defended myself, instinctually). They could have waited for me to finish the call. They could have waited to see if I calmed myself. I was not hurting anyone or even threatening anyone or myself with harm. All that I had done, in terms of physical threats, was to throw a lightweight chair at the wall. And that, it was clear to everyone, was intended not as a threat to anyone. Furthermore, it was done and over with. I had left that area and gone to my room. I had then come back and now sat on the chair by the phone, speaking to my interlocutor on the other end. There was no need to pick a fight or encourage a struggle. A wait-and-see policy could have successfully guided the situation to a better resolution not only for the situation at hand but for the entire hospital stay. As the poem by Dylan Thomas goes: “After the first death, there is other.” Once they decided to use four—point restraints, there was no going back. The first time broke everything, So they used them again, and again, and more and more freely and without justification but for convenience and punishment.
Back to Feb 5 or 6, after sleeping for six hours, I was taken out of restraints conveniently just in time for a visit from Dr. Angela Cappiello, my outside psychiatrist. Observed by my 1:1 monitor, I only dared whisper and dared not tell the doctor the full extent of the abuse that had been happening. Nevertheless, she took one look at Amy Taylor MD’s behavioral treatment plan posted on my wall, and told me that it would be impossible for anyone, even someone who was well, to follow it properly. She was so worried about me, and about my ability to complete the treatment plan’s requirements, even for the required “24 hours,” that she intervened. The next day, the single day that Dr. Taylor planned to be out of town, Dr. Cappiello asked Dr. Mehendru to evaluate me for discharge, telling her that she feared a power struggle had been set up that I could never win.
When Dr. Mehendru came to see me, at first I was angry, as the chart indicates, thinking she was just another Taylor flunky, preparing to use more restraints and seclusion, But when she asked if I would like to go home, I took one look at her, saw sincerity in her eyes, and burst into a smile, ready to say yes to anything. Miraculously “cured,” I left the IOL that very same day, less than 12 hours after being released from 4-point restraints and not 4 hours out of seclusion.
However, I was not well. Within two weeks time, I was back in the hospital, this time admitted to Yale New Haven Psychiatric Hospital, via their emergency room. Over the next 3 weeks I experienced an entirely different kind of care. At Yale I did not find a staff ready to fight or try to seclude or restrain me.
I was still the same person with the same problems, loud and angry at times, even “violent” to property in my frustration, and still psychotic, yet they never responded with a show of force. Why would they? At Yale it would be absolutely anathema to deliberately frighten a patient. What would be the purpose in that, they would think. They also never pushed me into a seclusion room or strapped me down in punitive 4-point restraints, or any of the other ill-advised responses that my PAD explains are the worst things to do to anyone who is struggling, scared and paranoid. In point of fact, Yale Psychiatric Hospital’s Washington Square unit does not have a seclusion room. They also have a “restraints-free” policy, so they didn’t use those at all either.
The Institute of Living on the other hand with its “We only use restraints and seclusion if we have to” policy, restrained me countless times, and for many more hours than was even legal. When I woke up that last morning, the room opposite me was occupied by yet another person in 4-point restraints! That is because once you allow staff to use restraints a little, it only takes a little to use them a lot. And once you sanction the use of restraints and seclusion at all, it is only time before someone abuses them and abuse becomes the norm.
I would like your response to this letter, I have sent it to many people within the state government and outside of it, But you may have the first response. Also you may be interested in the youtube video of my artwork which can be found at this site:
Prior to when you allowed the staff to body bag and restrain me, when I had done nothing wrong but leave the non seclusion quiet room, and you refused to come to my assistance, you had asked to see my artwork. Instead you left me to be tortured. Well, here is some of the art you might have seen had you rescued me from my abusers.:
Sincerely
Pamela Spiro Wagner
The final one you never saw in featured in the post below this one.
I have been diagnosed with schizophrenia for nearly forty years and was forcibly medicated and involuntarily hospitalized many times over those decades. Ordering me to take an “anti-psychotic” medication and then physically compelling me to submit to IM injections never got me to a point where I saw the “error of my ways” much less helped me to recover. How can that be? Take my 3-week stay at Yale New Haven Psychiatric Hospital in the summer of 2013. Because I refused the prescribed Zyprexa, I was repeatedly held down and forcibly injected with IM Haldol, a so-called first-generation “anti-psychotic.” Call Haldol an antipsychotic if you will or be honest and just call it a behavioral management drug, it subdued me, yes, it did indeed. It stupefied me. And in the end I cried “Uncle.” But before I surrendered and submitted to their demands, I only got worse, regressing to a degree so pathetic I find it hard to believe it now. But that this happened was a connection the doctors and staff never made,, not even when after I was forcibly injected, I would strip, defecate and write on the wall with my feces.
It seems obvious, at least from my experiences, long and manifold, that involuntary treatment does not work, at least not the way people think it will or should. Over the short run, you can indeed make a person take medication (which is what this is all about in the end, drugs, not something like psychotherapy being forced on anyone…). You can threaten a person with hospitalization “or else,” and frighten her into swallowing pills. And if she does refuse, you can hospitalize someone for refusing and medicate her against will just as you do now to certain in-patients.
You can, if coercion is your game, put certain involuntary in-patients into 4-point restraints, pretending that her very resistance makes her a danger to others, punishing her for fighting the team that holds her down. You can even inject her with so-called “depot” drugs that once in the system continue to work for as long as a month.
Clearly, people break, faced with threats and coercion and many eventually come to accept treatment “voluntarily,” at least for a time. They may even appear to “get better”. Nevertheless this sort of improvement is often shaky at best.
Involuntary — forced — treatment is the worst possible thing you can do to a person with a serious psychiatric condition, especially schizophrenia. Symptom improvement will likely be temporary, even with medication “on board.” I have yet to meet anyone who actually gained that magical “insight” via coerced medication… And given the side effects of all the known drugs, very few people who are not voluntarily in the system consent to take them for long — for good reason.
Moreover, as recent research has shown, there is every reason to suspect that psychoactive drugs, especially the so-called antipsychotic drugs, are far less efficacious in promoting real and permanent recovery than we have been told. However, the effects of trauma and the aftermath of involuntary treatment can be disabling, even permanent. I know; I have been there. As a result of my experiences with forced treatment I now suffer from PTSD in addition to the diagnosis of schizophrenia.
Although at present I choose to attend outpatient treatment, I do not always comply with taking medication, especially when it make me feel bad. I won’t even take meds that others claim alleviate my symptoms. If a drug makes me feel horrible inside, I assert the right to refuse it. Sometimes treatment can be worse than the disease. Alas, because of this, I have, while in-patient, all too frequently been subjected to forced medication hearings, hearings which I believe I was pre-determined to lose, the deck being stacked against me.
At the former Hospital of St Raphael’s in New Haven in 2004, I was not only forced to take the atypical antipsychotic drug Zyprexa, despite the fact that the medication had caused me to gain 60 pounds, elevated my cholesterol and triglycerides sky-high, and made me pre-diabetic. The probate judge, on the instigation of my in-patient psychiatrist, also ordered that I undergo involuntary ECT otherwise known as electro-shock treatments. I was so terrified of the side effects and the real brain damage ECT was inflicting on me, that I literally awoke,mornings, with excrement in my underwear.
In the more recent past, my experience at Manchester Memorial Hospital ECHN in Manchester, CT was just as horrendous. This, along with an equally brutal experience, at Middlesex Hospital in Middletown, Connecticut 6 months later combined to such trauma that I was diagnosed with the additional problem of PTSD. As recently as the winter of 2013, at Hartford Hospital’s Institute of Living, I was threatened with forced ECT, kept in seclusion for three weeks and restrained for nearly twenty hours multiple times. Why? Because as the record states, I was unpredictable and “did not follow directions.”
I would like to tell you about the Manchester Hospital experience in a little detail, as I believe it will give you a “taste” of where IOC, when taken to its logical conclusion, can and will lead.
I was admitted there on a 15-day physician’s emergency certificate (PEC), and the attending, a certain Dr Benjamin Zigun, summarily took me off the two-antipsychotic drug combination, plus an anti-seizure medication and the anti-depressant I had come in on. This drug “cocktail” had worked for me since 2007 without distressing side effects. I was not only willing to take it but I felt it helped me function better than I had in years. But the psychiatrist at Manchester Hospital decided, and I quote, “since you are here, by definition your current meds aren’t working. I will put you on something else.” Did it matter to him that I had already been tried on nearly every other drug on the market, old and new, and none worked as well and with as few side effects as the Abilify/Geodon combination I was then taking? No, he was the doctor and the doctor’s decree was law.
As a result of his ministrations, the “offending meds” were removed and I was again ordered to take Zyprexa, despite its known and severe side effects. Over the next few days, I continued to refuse it. Naturally, having been abruptly withdrawn from all my usual medications, I began to decompensate further, having nothing in my system. A forced medication hearing was held. For some reason, Dr Zigun decided I would not be given Zyprexa after all, but one of the oldest neuroleptics in the PDR, Trilafon. When I objected, he said only that if I refused even a single dose, I would be injected in the buttocks with 5mg Haldol.
All too familiar with Trilafon’s side effects — from akathisia’s maddening restlessness to a constant fine tremor in my fingers, I refused to swallow the pills. But neither would I willingly lie down to take a needle full of “vitamin H,” Haldol being a drug just as awful as Trilafon if not worse. So I resisted, physically, when it came to the nursing staff grabbing me and pinning me to the floor. I fought them when they so much as approached me with the punishment hypodermic.
At first, they just overpowered me, injected me and walked away. But after a few such tussles they started calling “a code” to bring in the goon squad. I do not know how many times this happened but the goon squad consisted of several people including uniformed security guards . Without a pause, they would barge into the room, assault, restrain and inject me, despite my terrified screams.
This sort of violent encounter happened so many times, along with predictable and regular use of 4-point restraints and/or solitary confinement, where I would be locked in their dark, cold seclusion room, that I literally lost track of time. Indeed, but for whatever I managed to record in my journal after each episode, and from their single-viewpoint one-sided hospital chart, I would have no idea what happened during most of that entire three week period at Manchester Hospital, though from my bodily reaction when thinking about it, I know something very bad happened.
Why do I tell you this? Because this sort of aggression, even torture is what forced medication and involuntary treatment lead to much more often than you may want to believe.
If H.R. 4302 passes in the Senate and expanded IOC is instituted in the states where it is now allowed, how precisely do people intend to treat a person with a “mental illness” who does not to want treatment? If a person refuses to leave her apartment to be hospitalized, and is able bodied and physically strong, do they propose to assault, even Taser her, though innocent of a crime? Once she is unconscious and no longer able to resist, do they then intend to hospitalize her against her will so that she can be forcibly medicated, with the threat of 4-point restraints as a back-up if she continues to resist. Or perhaps they expect that trauma itself to scare any individual into compliance?
I am not against all psychiatric treatment. I am definitely not against all psychiatric residential treatment facilities ( including hospital psych units…) But we have curtailed the availability of in-patient beds at present to our detriment, even as we have allowed drug company research scientists and providers to focus almost to the point of tunnel vision on the medical model. This has brought us right to this notion that if we institute IOC, and can force a given individual to take medication, we will be working on a problem that has a real and objectively verified solution. In point of fact, however, there is absolutely no proof that antipsychotic drugs lower violence on the streets or have any effect at all on the incidence of violent crime. That said, if a national IOC law mandated forced treatment, and hospitalization, where are the psychiatric beds to follow through on that mandate? Downsized, in most states to ghosts of their former abundance.
If this is what supporters of H.R, 4302 anticipate and believe in: IM injections, four-point restraints and all, then I must ask: When will you learn that you cannot treat anyone with violence and expect the outcome to be a desirable one? What you propose to do is to subject persons with psychiatric disorders to more trauma and violence than ever. You want to expose them to a“treatment” that is just euphemism for brutality.
I fought back, tooth and nail, biting and clawing the goon squads that descended upon me and attacked me, intending to shackle me by the wrists and ankles to a bed, because as they told me, “ I didn’t follow directions. Yes, I resisted. Who would not have? I was terrified. What did they expect me to do, politely thank them?
This sort of coercion and cruelty masquerading as care doesn’t help anyone get better, it only chases them the heck out of Dodge and as far away from “treatment” as they can get. Oddly enough, little do “Escapees” from treatment such as these know that they might be the lucky ones. As longitudinal studies of treated and untreated individuals with schizophrenia are coming to light, it has become apparent –even Thomas Insel, head of the NIMH admitted this on his blog — that treating – medicating — schizophrenia long-term has had unintended consequences, one of which has been to inhibit complete recovery. By contrast, those persons who walked out or were forced out of treatment, “back wards patients,” seemingly hopeless — it turns out that these people to a much greater degree than those who stayed in the system, recovered on their own, without help, largely by stopping their medications.
A majority of these “lost souls” found themselves only after they ceased taking medication and ceased consuming mental health services. Because they became wage-earning, productive citizens and not mental health service users, many are now “lost” to the mental health system. To experience so few symptoms as to be unknown the to provider community despite past illness, surely this must be accounted the best of all possible outcomes.
IOC works — or doesn’t work — according to a medical model that imposes medication on the unwilling, with no end point, insisting that mental illness is no different from diabetes. But as Dr Insel has admitted, this is not true and apparently never was. New models are needed. Violence is no solution, nor does it cure anyone to impose treatments of dubious value and great harm on those who are different from some mythical “norm. ”
(I sent a version of this to Connecticut’s Senator Blumenthal and several other people, including the New York Times, without response, so I am posting it here for public consumption and comment.)
Kelli being Drawn by Artist, in Fractured Colors – a blind contour study filled with color
I received the announcement below from Kayla Bowen today and thought I would pass it on. Dreamrly’s COLLECTIVE magazine is available either in print on demand or in a digital format. While I am one of the featured artists / poets, that is not the only reason I publicize the launch. I believe that dreams speak volumes, both to us and about our selves, and if we learned to listen to them, we might learn a great deal…
COLLECTIVE 2014 Launch Edition is Now Available
Launch edition 2014 features 108 full color pages, including:
Submissions from 40 contributors from all over the world
Three distinct galleries of visual art work
Interview with archetypal dreamwork analyst Laura Smith
Collaborative dreamwork feature with blogger Rita Kowats
An excerpt from Painted Over White, a novel by Katie Abrams
An excerpt from The Magic Pattern screenplay by Maria Isabel Pita and Dr. James Kroll
If you are in the Nashville, Tennessee area, consider coming out to join us Sunday, April 6 from 2 – 4 pm at Art & Soul on 12th Avenue.
Copies of the magazine and launch poster will be available for purchase. We’ll have snacks, networking with other dream and creative arts enthusiasts, two interactive dream art stations, and an opportunity to see the cover art installation and meet cover artist Wayne Brezinka in person.
COLLECTIVE is launching a poster series to raise funds for the magazine and to raise awareness about dream work and the visual arts.
The launch poster is available now on the web site.
COLLECTIVE is also hosting a poster design contest to select three additional poster designs to complete the series. Winners will receive $50 and 5 poster prints of their design.
Are you interested in submitting your design for the series? Learn more.